
Overview
Deep brain stimulation (DBS) is a safe, effective, and well-established therapy for neurologic disorders like Parkinson's disease, essential tremor, dystonia, and epilepsy.
I have a particular interest and extensive experience in DBS, and I am the director of functional neurosurgery at HCA HealthONE Swedish. I perform 200+ movement disorder surgeries a year.
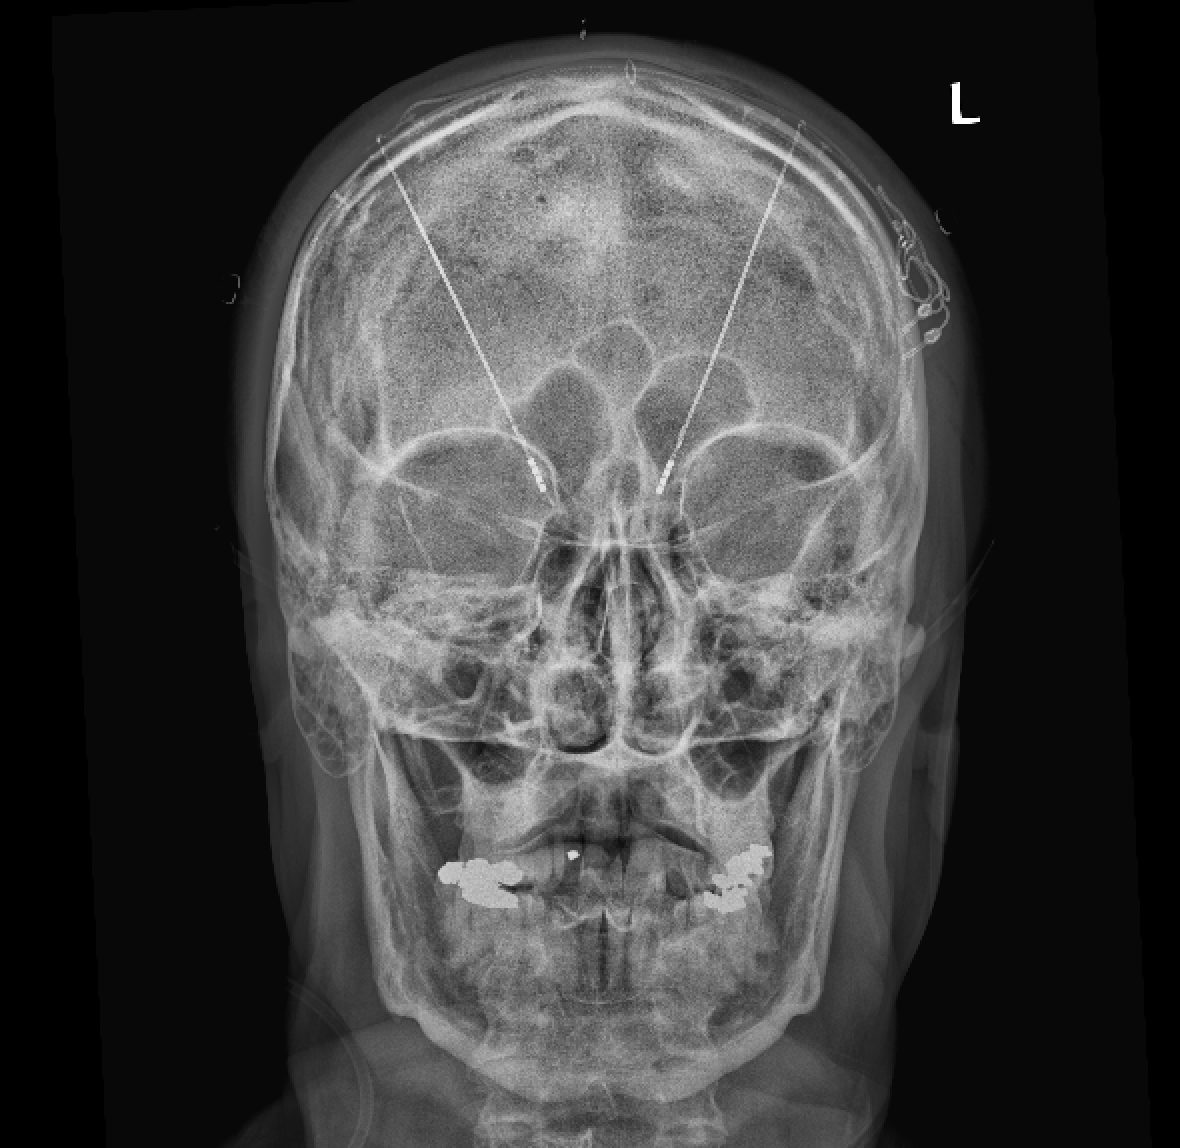
In a DBS procedure, I insert one or two thin wires into the brain and connect it to a small battery that is implanted under the collarbone, similar to a pacemaker. The system delivers painless electrical pulses.
DBS has been used in the United States for 25 years for Parkinson's disease and 30 years for essential tremor. Clinical trials have shown improvements in movement in Parkinson's disease, essential tremor, and dystonia, and fewer seizures in epilepsy. A consistent benefit across all of these disorders is that patients who receive DBS report a better quality of life. DBS is not a cure, however, so symptoms may not disappear completely.
The DBS system sits entirely beneath the skin, and in most patients it is not visible from the outside during daily life.
Who DBS can help
Parkinson's disease. Studies have shown improvement in tremor, stiffness, slowness, and other motor (movement) symptoms. Patients gain more time at their best motor function (an additional 4-5 hours a day), need lower doses of Parkinson's medication, and do better with activities of daily living.
Essential tremor. The average patient can expect an 85-90% reduction in hand and arm tremor.
Dystonia. For patients with severe symptoms despite oral medications and Botox, DBS is often very effective at reducing dystonic movements.
Epilepsy. DBS can reduce seizures by an average of over 70% long-term in carefully selected patients with partial onset (focal) seizures.
Is DBS right for me?
The evaluation begins with a discussion between you, me, and your neurologist about whether DBS is right for you. Neuropsychological testing is always recommended before DBS. If you have Parkinson's disease, you will also need a levodopa sensitivity challenge, which compares your symptoms with and without your medication using a standard rating scale (UPDRS-III, ON and OFF).
At your appointment with me, I will review your medical history, symptoms, and test results, perform a physical examination, and discuss whether and how DBS might help you.
How I perform DBS
These are the questions patients ask me most often.
How often do you do DBS and similar procedures?
I perform 200+ movement disorder surgeries a year and an additional 50 epilepsy surgeries a year.
Awake or asleep?
I perform DBS with you asleep (general anesthesia).
What technique do you use?
I use a surgical robot (Rosa) to assist with placement of the leads. The surgical robot does not physically touch you during the surgery. I verify accuracy with a CT and electrode recordings in the operating room.
Which implant and device vendor do you use?
I use all three vendors (Medtronic, Boston Scientific, and Abbott). I will implant using the manufacturer you and your neurologist prefer, and I provide guidance, as needed.
What is your infection rate?
Roughly 1%.
Surgery and recovery
If you decide to proceed with DBS, I will order an MRI and CT scan of your brain to plan the surgery. Implanting DBS takes two separate procedures, and I perform both with you asleep.
Brain wires
- I implant one or two tiny wires (just over 1 millimeter) into the brain, assisted by a surgical robot to improve accuracy.
- Most patients stay one night in the hospital and go home the following morning.
Battery
- I implant a small battery just under the collarbone, usually 1-3 weeks after stage 1.
- It is outpatient surgery, meaning you go home the same day.
Most patients can resume normal activity fairly quickly after surgery. I advise avoiding strenuous exercise and heavy lifting for 2-4 weeks, but you can continue with most of your normal daily activities.
After 4 weeks, your neurologist will turn on the stimulator. Most patients need several neurology appointments, usually spaced a few weeks apart, to get the settings just right. If your neurologist does not program DBS devices, I can connect you with a specialist who does.
If you are my patient and are considering or planning DBS surgery, my DBS guide for patients explains how to prepare and what to expect before and after surgery. If you are planning a battery replacement, please see my guide for DBS battery replacement.
Questions to bring to your visit
- Am I a good candidate for DBS, and what would I realistically expect it to improve?
- Which brain target do you recommend for me, and why?
- Would you recommend treating one side of the brain at a time or both sides at the same time?
- Which device would suit me, and who will program it?
- Which risks matter most in my situation?
If you live near Denver and have essential tremor, Parkinson's disease, dystonia, or epilepsy, please consider meeting me in consultation to learn more about your treatment options.