
What is cervical radiculopathy?
Cervical radiculopathy refers to symptoms from compression of one or more of the nerve roots that arise from the spinal cord in the neck and travel down into the arm. Symptoms may include pain that radiates down the arm or into the shoulder or shoulder blade, weakness of arm muscles, a loss of sensation (numbness), and tingling in the arm or hand. Patients may have just one or any combination of the above symptoms.
What causes cervical radiculopathy?
The cause of cervical radiculopathy is compression of a spinal nerve near where it emerges from the spinal cord in the neck. This can be due to a herniated disc or disc bulge, degenerative arthritis, a vertebral fracture, spinal instability, or other problems.
How is cervical radiculopathy diagnosed?
Cervical radiculopathy can usually be diagnosed with a careful history and physical examination and an MRI scan and X-rays of the neck. In some cases, additional studies such as an EMG may be needed.
Can cervical radiculopathy improve without surgery?
Cervical radiculopathy due to certain causes may improve or even resolve over weeks to months without the need for surgery. Some cases do not improve with time - even with medications, injections, and physical therapy. Surgery should be considered for patients with persistent, bothersome symptoms despite non-surgical treatments.
Is surgery likely to help?
For patients with persistent and bothersome symptoms from cervical radiculopathy, surgery is often a definitive treatment option. Most patients who undergo surgery for cervical radiculopathy can expect their symptoms to improve or resolve. Some symptoms may take longer than others (for example, numbness tends to take longer to improve than pain). There are surgical options from both the front and the back of the neck (i.e. “anterior” and “posterior”).
What are the surgical options?
Anterior surgery is used more commonly for cervical radiculopathy. Options include anterior cervical discectomy and fusion (ACDF) and cervical disc replacement (arthroplasty). Posterior approaches include cervical laminectomy/foraminotomy, with or without posterior cervical fusion, CORUS cervical fusion, and cervical laminoplasty.
If you are considering or planning an ACDF or a cervical disc replacement, my ACDF guide and cervical disc replacement guide for patients explain how to prepare and what to expect before and after surgery.
How do you decide which surgery is right for me?
Each of these options has benefits and drawbacks. The right option for you will depend on your symptoms, the number of spinal levels affected, and factors related to your spinal anatomy, medical and surgical history, tobacco use, and age.
Example MRI of a Pinched Nerve in the Neck
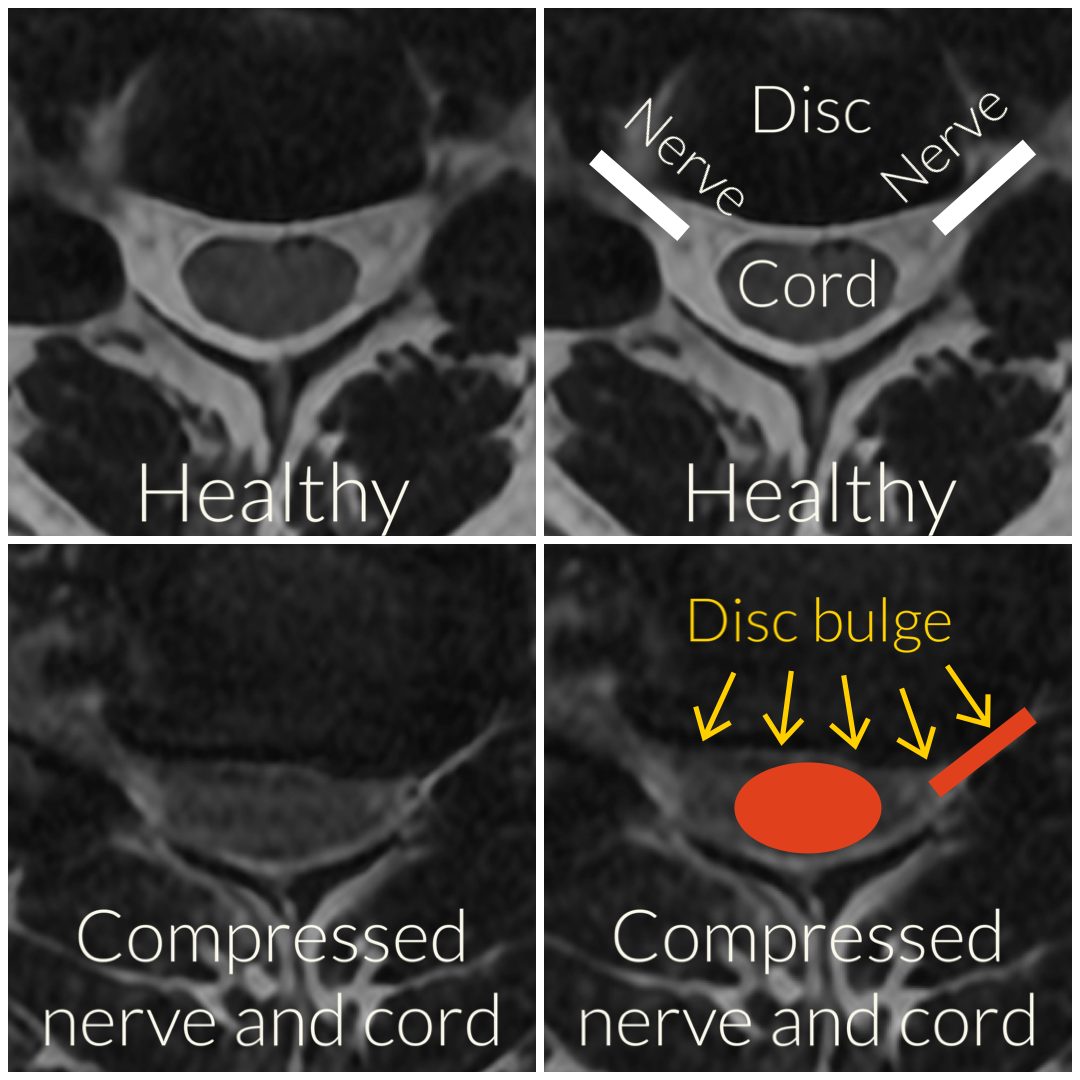
Example MRI (top panels) showing a healthy disc, spinal cord, and nerve roots, and a second MRI (lower panels) showing a disc bulge (yellow arrows) causing compression of the spinal cord and a nerve root. Note that the bright rim of spinal fluid (CSF) cushioning the spinal cord in the top panels disappears due to the disc bulge.
Should I meet with you?
If you live near Denver and are suffering from cervical radiculopathy, please consider meeting me in consultation to learn more about your treatment options. You can also review my ACDF guide and my cervical disc replacement guide for patients.